Contents
- Healthcare Infrastructure
- Medical Education & Research
- Government Medical College
- Age-Old Practices & Remedies
- Graphs
- Healthcare Facilities and Services
- A. Public and Govt-Aided Medical Facilities
- B. Private Healthcare Facilities
- C. Approved vs Working Anganwadi
- D. Anganwadi Building Types
- E. Anganwadi Workers
- F. Patients in In-Patients Department
- G. Patients in Outpatients Department
- H. Outpatient-to-Inpatient Ratio
- I. Patients Treated in Public Facilities
- J. Operations Conducted
- K. Hysterectomies Performed
- L. Share of Households with Access to Health Amenities
- Morbidity and Mortality
- A. Reported Deaths
- B. Cause of Death
- C. Reported Child and Infant Deaths
- D. Reported Infant Deaths
- E. Select Causes of Infant Death
- F. Number of Children Diseased
- G. Population with High Blood Sugar
- H. Population with Very High Blood Sugar
- I. Population with Mildly Elevated Blood Pressure
- J. Population with Moderately or Severely High Hypertension
- K. Women Examined for Cancer
- L. Alcohol and Tobacco Consumption
- Maternal and Newborn Health
- A. Reported Deliveries
- B. Institutional Births: Public vs Private
- C. Home Births: Skilled vs Non-Skilled Attendants
- D. Live Birth Rate
- E. Still Birth Rate
- F. Maternal Deaths
- G. Registered Births
- H. C-section Deliveries: Public vs Private
- I. Institutional Deliveries through C-Section
- J. Deliveries through C-Section: Public vs Private Facilities
- K. Reported Abortions
- L. Medical Terminations of Pregnancy: Public vs Private
- M. MTPs in Public Institutions before and after 12 Weeks
- N. Average Out of Pocket Expenditure per Delivery in Public Health Facilities
- O. Registrations for Antenatal Care
- P. Antenatal Care Registrations Done in First Trimester
- Q. Iron Folic Acid Consumption Among Pregnant Women
- R. Access to Postnatal Care from Health Personnel Within 2 Days of Delivery
- S. Children Breastfed within One Hour of Birth
- T. Children (6-23 months) Receiving an Adequate Diet
- U. Sex Ratio at Birth
- V. Births Registered with Civil Authority
- W. Institutional Deliveries through C-section
- X. C-section Deliveries: Public vs Private
- Family Planning
- A. Population Using Family Planning Methods
- B. Usage Rate of Select Family Planning Methods
- C. Sterilizations Conducted (Public vs Private Facilities)
- D. Vasectomies
- E. Tubectomies
- F. Contraceptives Distributed
- G. IUD Insertions: Public vs Private
- H. Female Sterilization Rate
- I. Women’s Unmet Need for Family Planning
- J. Fertile Couples in Family Welfare Programs
- K. Family Welfare Centers
- L. Progress of Family Welfare Programs
- Immunization
- A. Vaccinations under the Maternal and Childcare Program
- B. Infants Given the Oral Polio Vaccine
- C. Infants Given the Bacillus Calmette Guerin (BCG) Vaccine
- D. Infants Given Hepatitis Vaccine (Birth Dose)
- E. Infants Given the Pentavalent Vaccines
- F. Infants Given the Measles or Measles Rubella Vaccines
- G. Infants Given the Rotavirus Vaccines
- H. Fully Immunized Children
- I. Adverse Effects of Immunization
- J. Percentage of Children Fully Immunized
- K. Vaccination Rate (Children Aged 12 to 23 months)
- L. Children Primarily Vaccinated in (Public vs Private Health Facilities)
- Nutrition
- A. Children with Nutritional Deficits or Excess
- B. Population Overweight or Obese
- C. Population with Low BMI
- D. Prevalence of Anaemia
- E. Moderately Anaemic Women
- F. Women with Severe Anaemia being Treated at an Institution
- G. Malnourishment Among Infants in Anganwadis
- Sources
HINGOLI
Health
Last updated on 19 October 2026. Help us improve the information on this page by clicking on suggest edits or writing to us.
Hingoli’s healthcare landscape, like many other regions across India, is shaped by a mix of indigenous and Western medical practices. For centuries, indigenous knowledge and treatments provided by practitioners such as hakims and vaidyas have formed the foundation of healthcare in the region. This long-standing relationship between communities and their natural environment played a key role in shaping the district’s early medical traditions. Over time, its landscape has gradually evolved with the introduction and expansion of more specialized medical services.
Healthcare Infrastructure
Much like other regions in India, Hingoli’s healthcare infrastructure follows a multi-tiered system that involves both public and private sectors. Currently, the public healthcare system is tiered into primary, secondary, and tertiary levels. Primary care is provided through Sub Centres and Primary Health Centres (PHCs), while secondary care is managed by Community Health Centres (CHCs) and Sub-District hospitals. Tertiary care, the highest level, includes Medical Colleges and District Hospitals. This system has been shaped and refined over time, influenced by national healthcare reforms.

Supporting this structure is a network of Accredited Social Health Activists (ASHAs) who, as described by the National Health Mission, serve as “an interface between the community and the public health system.” Over time, this multi-layered healthcare model has been continuously shaped and refined by national healthcare policies and reforms to improve universal health coverage across regions.
Hingoli’s formal healthcare infrastructure, like much of India, has its origins in the colonial era, which laid the groundwork for the system in place today. As Rama Baru explains in Missionaries in Medical Care (1999), “Allopathic medicine was introduced by the British in the mid-18th century, primarily to serve the needs of their civilian and military population.” Interestingly, during this time, Hingoli was part of the Nizam’s Hyderabad State and served as an important military base and cantonment area. The presence of the military in the district likely played a key role in the establishment of dispensaries throughout the region and many military and veterinary facilities were established to serve the needs of stationed troops.
Hingoli’s medical infrastructure remained limited for many decades. According to the 2001 Census, only 171 of the district’s 672 villages then had access to any form of medical facility. Over the years some change has taken place, The public health infrastructure began expanding. Additionally, in the 21st century, private hospitals started to emerge in the district; with their establishment being driven by trusts, NGOs, and locals themselves.
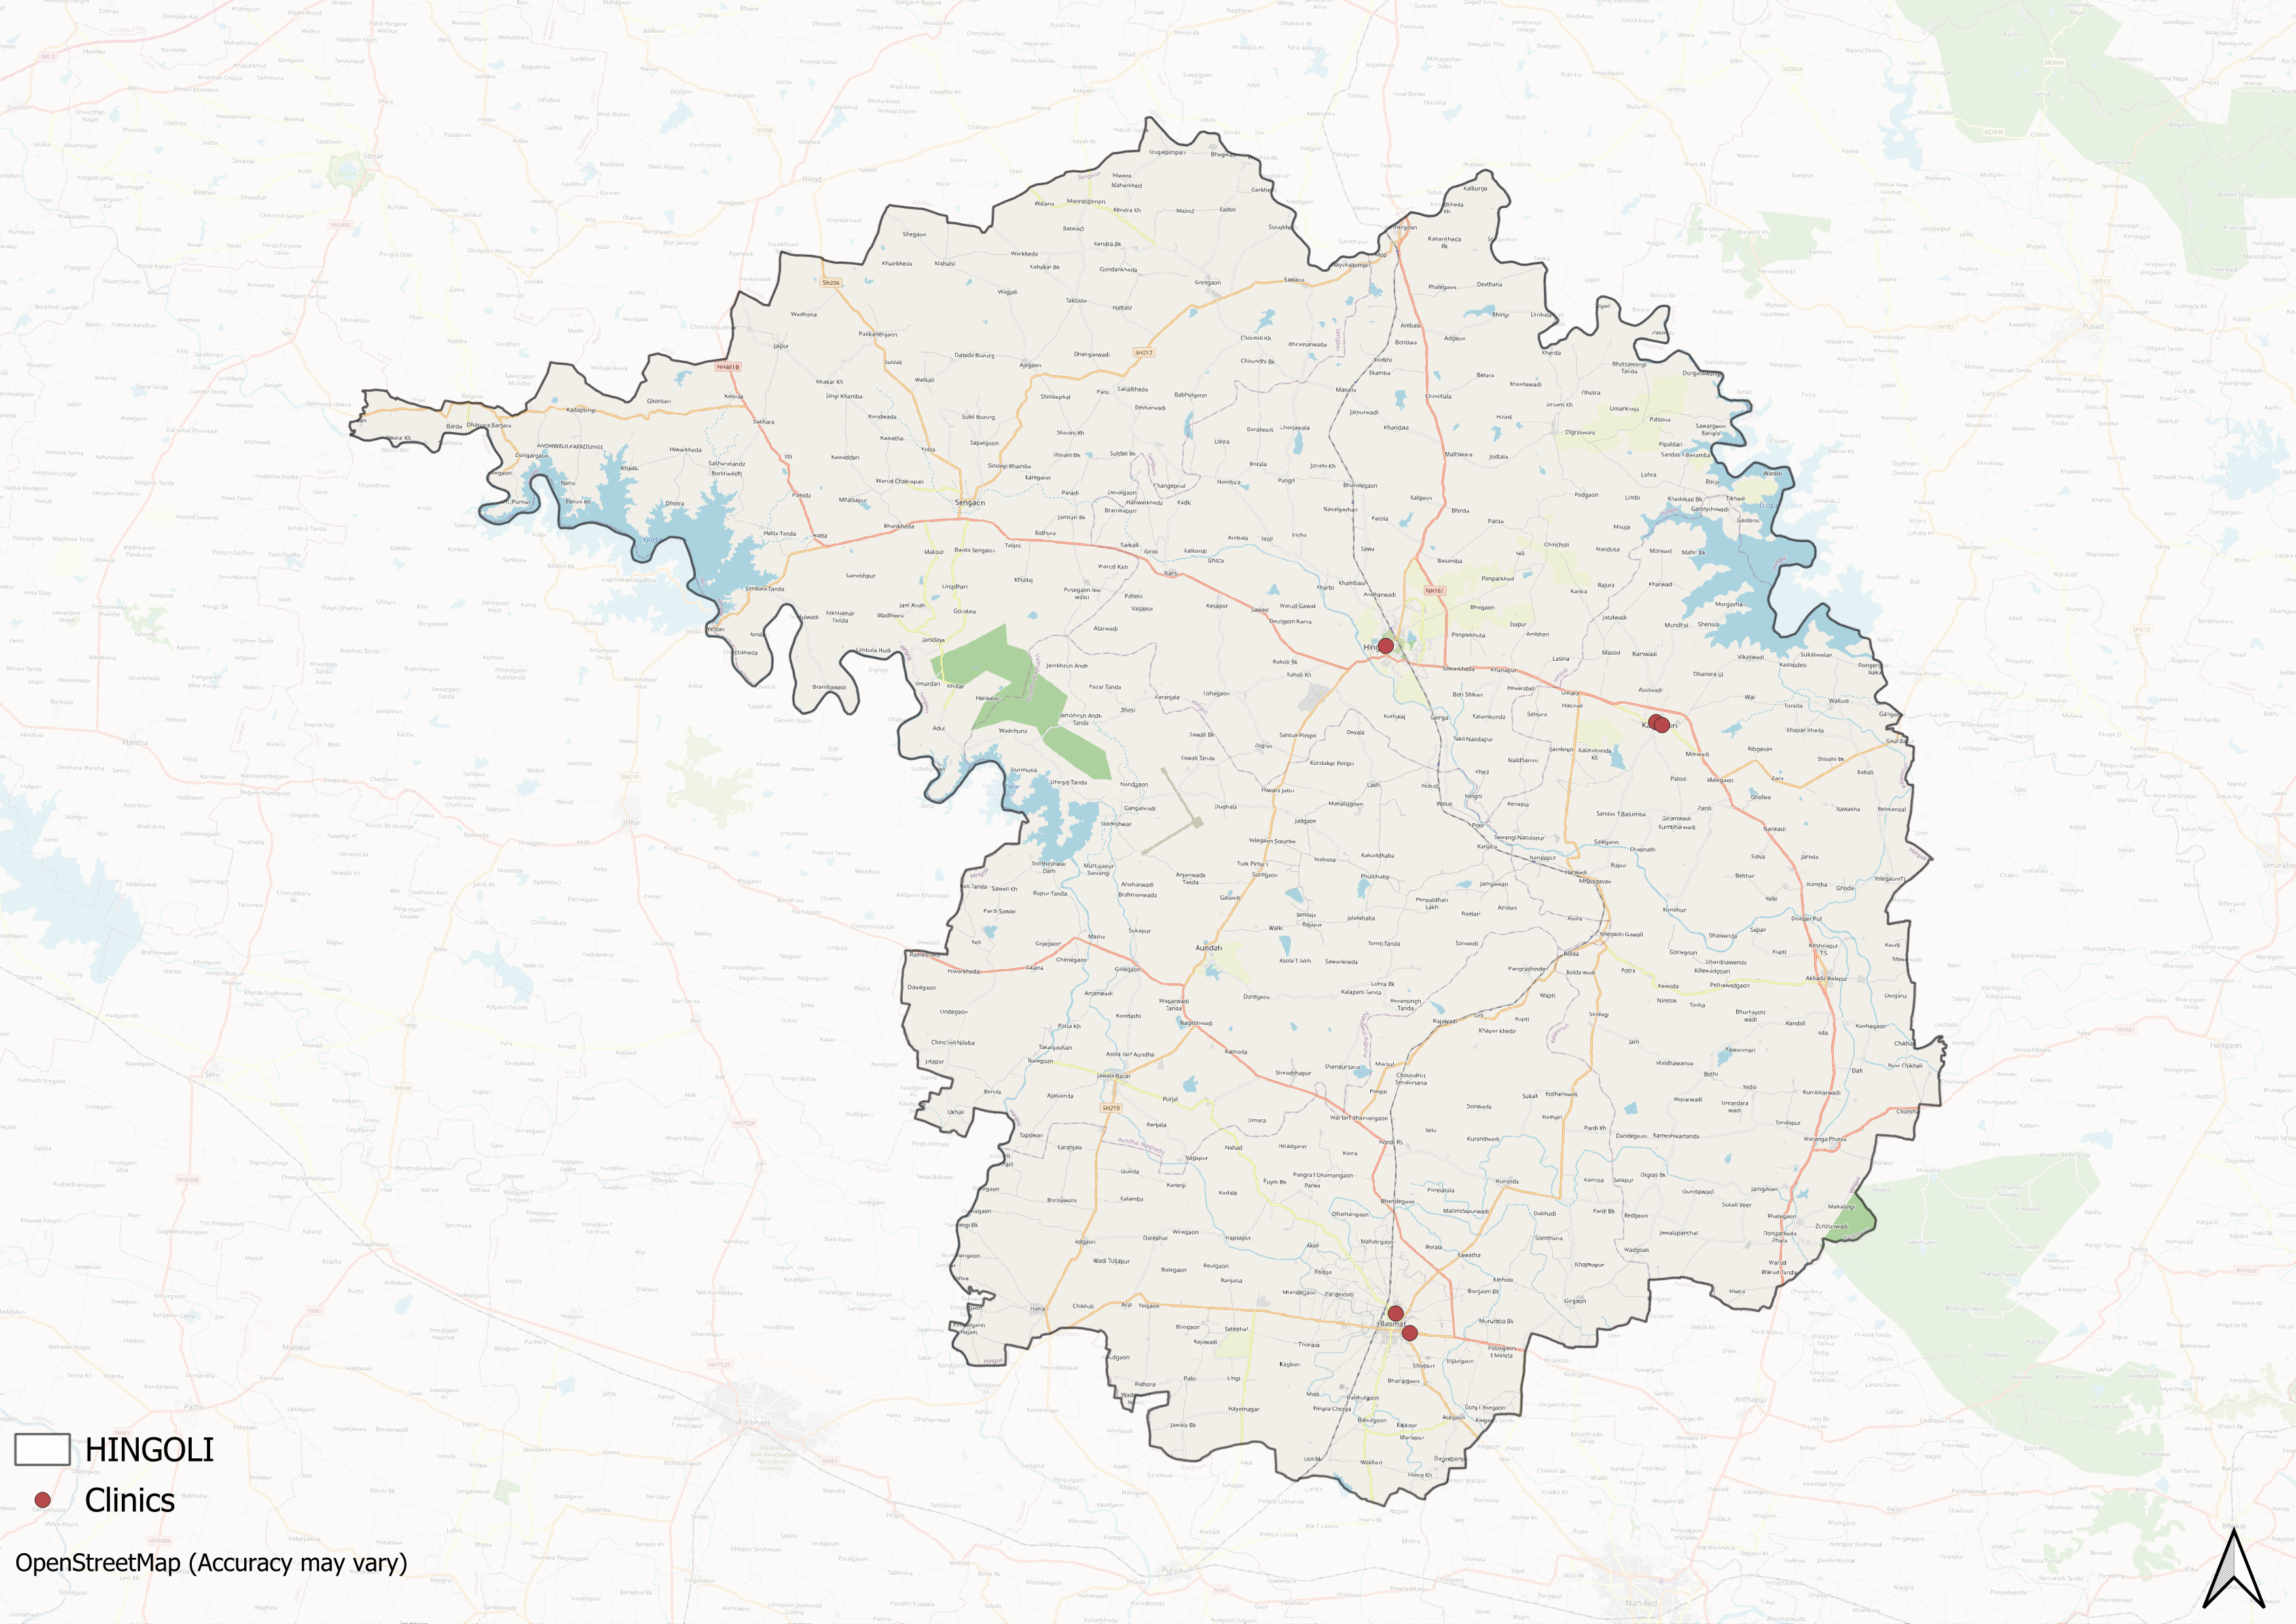
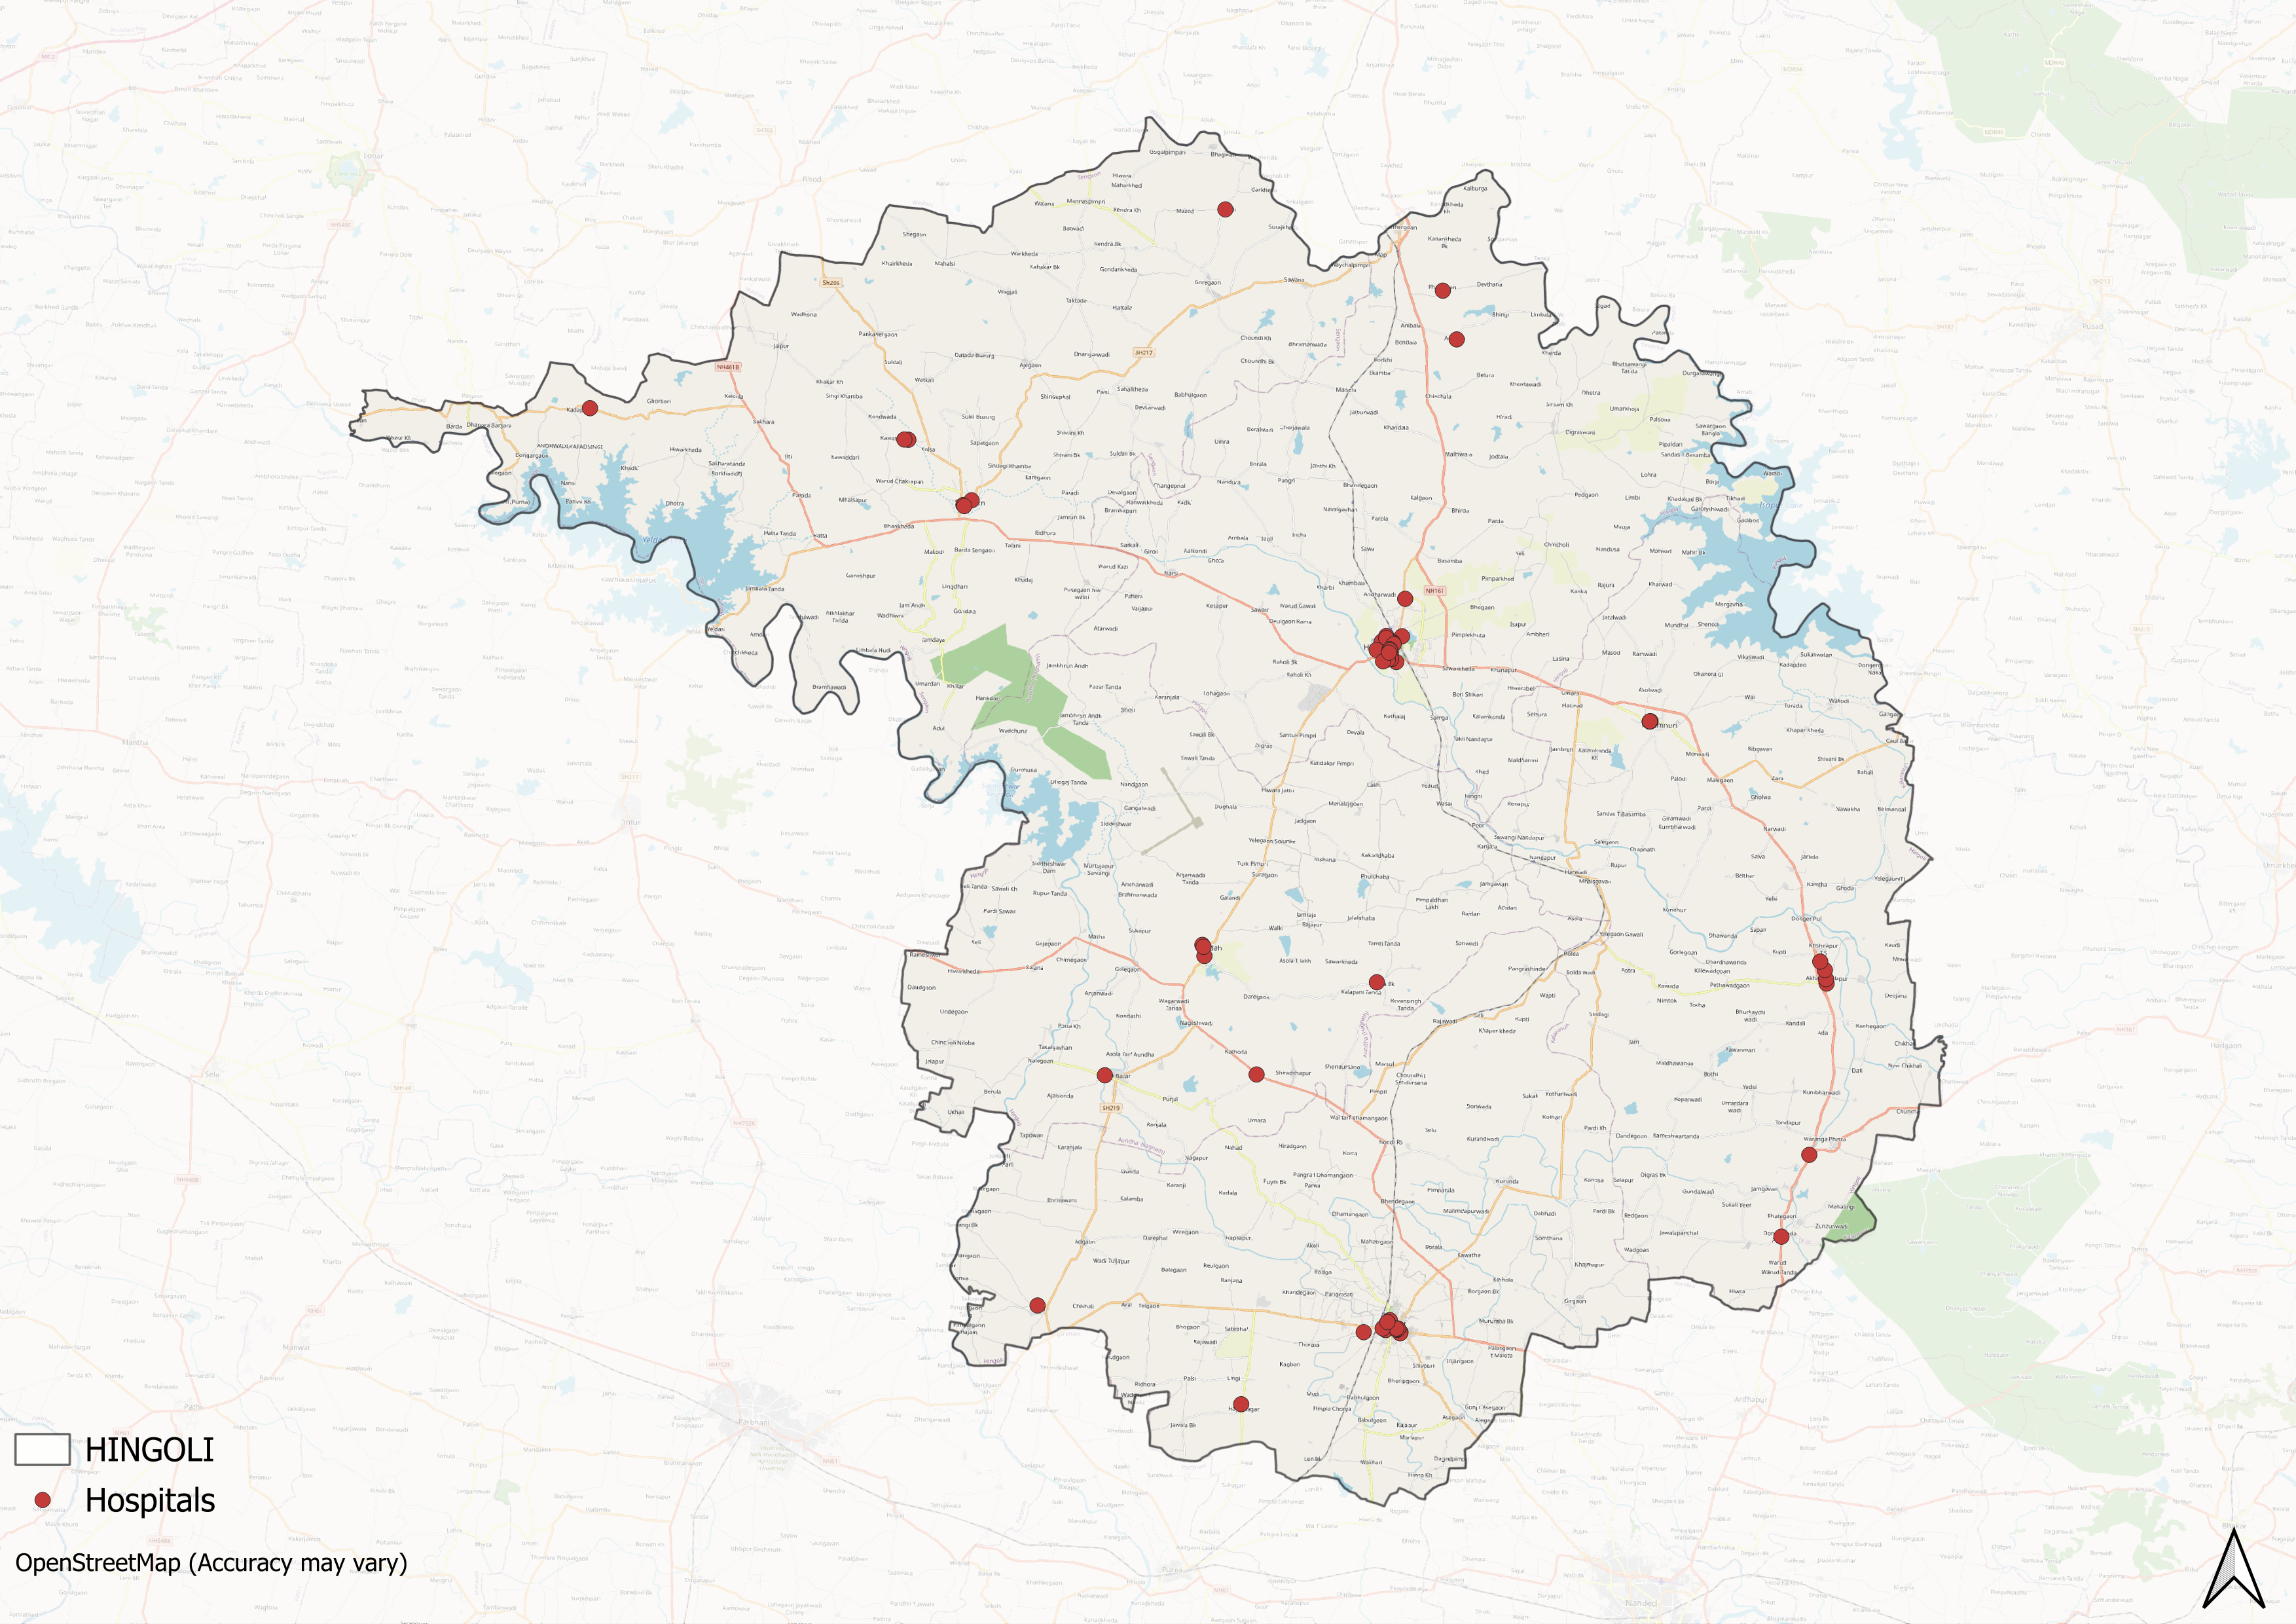
The district has seen the establishment of multispecialty and superspecialty facilities, particularly in Hingoli city. Among the notable additions is an Antiretroviral Therapy (ART) Centre, which provides dedicated care for individuals living with HIV/AIDS. Notably, Hingoli became the first district in Maharashtra to establish such a centre.
Medical Education & Research
Medical education and research are foundational to a district’s healthcare infrastructure. As Mathew Gerge aptly highlights, medical institutions often serve a “dual purpose,” which includes educating future healthcare professionals and providing healthcare services to the local population. When it comes to Hingoli, facilities dedicated to medical education appear to remain limited here, though recent developments mark important progress.
Government Medical College
Government Medical College, Hingoli is a government-run medical institution located in the Hingoli district of Maharashtra. Established in 2024, the college is affiliated with the Maharashtra University of Health Sciences (MUHS), Nashik, and is approved by the National Medical Commission (NMC). The institution offers an undergraduate MBBS program in the field of medicine.
Age-Old Practices & Remedies
Before the development of a formal three-tiered healthcare system, communities in Hingoli, like much of India, depended on indigenous knowledge and local remedies for their health needs. India has long been characterised by a pluralistic health tradition, where household treatments, folk beliefs, and local healers coexisted alongside emerging modern systems. District Gazetteers of Maharashtra also often record how superstition and ritual shaped local approaches to illness and recovery.
In Hingoli, older residents recall practices once used to treat snake bites, such as the पंडाल (Pandal) ritual, which sometimes had severe outcomes. Neem leaves were placed near patients as indicators of their condition. For common ailments, local remedies included applying a paste of split chickpeas and curd for chickenpox and using sugarcane to diagnose jaundice based on changes in colour. Illnesses were frequently attributed to curses or spirits and were managed through household methods or consultations with folk healers.
Graphs
Please Note
- Some line graphs may start a few years before the data begins. We are fixing this.
- All data comes in financial years, but is graphed below in calendar years (2015 in our graph means FY 2015-16).
- The District Statistical Abstracts are in Marathi. Translations were done carefully, but some titles or details may differ. There may be some data entry errors. Please report any issues you find.
- Sometimes districts without data may show empty graphs. We've removed them but let us know if any remain.
- Some graphs may not render correctly. A hard refresh (Ctrl/Command +Shift +R) usually fixes this.
Healthcare Facilities and Services
A. Public and Govt-Aided Medical Facilities
Loading chart data...
B. Private Healthcare Facilities
Loading chart data...
C. Approved vs Working Anganwadi
Loading chart data...
D. Anganwadi Building Types
Loading chart data...
E. Anganwadi Workers
Loading chart data...
F. Patients in In-Patients Department
Loading chart data...
G. Patients in Outpatients Department
Loading chart data...
H. Outpatient-to-Inpatient Ratio
Loading chart data...
I. Patients Treated in Public Facilities
Loading chart data...
J. Operations Conducted
Loading chart data...
K. Hysterectomies Performed
Loading chart data...
L. Share of Households with Access to Health Amenities
Loading chart data...
Morbidity and Mortality
A. Reported Deaths
Loading chart data...
B. Cause of Death
Loading chart data...
C. Reported Child and Infant Deaths
Loading chart data...
D. Reported Infant Deaths
Loading chart data...
E. Select Causes of Infant Death
Loading chart data...
F. Number of Children Diseased
Loading chart data...
G. Population with High Blood Sugar
Loading chart data...
H. Population with Very High Blood Sugar
Loading chart data...
I. Population with Mildly Elevated Blood Pressure
Loading chart data...
J. Population with Moderately or Severely High Hypertension
Loading chart data...
K. Women Examined for Cancer
Loading chart data...
L. Alcohol and Tobacco Consumption
Loading chart data...
Maternal and Newborn Health
A. Reported Deliveries
Loading chart data...
B. Institutional Births: Public vs Private
Loading chart data...
C. Home Births: Skilled vs Non-Skilled Attendants
Loading chart data...
D. Live Birth Rate
Loading chart data...
E. Still Birth Rate
Loading chart data...
F. Maternal Deaths
Loading chart data...
G. Registered Births
Loading chart data...
H. C-section Deliveries: Public vs Private
Loading chart data...
I. Institutional Deliveries through C-Section
Loading chart data...
J. Deliveries through C-Section: Public vs Private Facilities
Loading chart data...
K. Reported Abortions
Loading chart data...
L. Medical Terminations of Pregnancy: Public vs Private
Loading chart data...
M. MTPs in Public Institutions before and after 12 Weeks
Loading chart data...
N. Average Out of Pocket Expenditure per Delivery in Public Health Facilities
Loading chart data...
O. Registrations for Antenatal Care
Loading chart data...
P. Antenatal Care Registrations Done in First Trimester
Loading chart data...
Q. Iron Folic Acid Consumption Among Pregnant Women
Loading chart data...
R. Access to Postnatal Care from Health Personnel Within 2 Days of Delivery
Loading chart data...
S. Children Breastfed within One Hour of Birth
Loading chart data...
T. Children (6-23 months) Receiving an Adequate Diet
Loading chart data...
U. Sex Ratio at Birth
Loading chart data...
V. Births Registered with Civil Authority
Loading chart data...
W. Institutional Deliveries through C-section
Loading chart data...
X. C-section Deliveries: Public vs Private
Loading chart data...
Family Planning
A. Population Using Family Planning Methods
Loading chart data...
B. Usage Rate of Select Family Planning Methods
Loading chart data...
C. Sterilizations Conducted (Public vs Private Facilities)
Loading chart data...
D. Vasectomies
Loading chart data...
E. Tubectomies
Loading chart data...
F. Contraceptives Distributed
Loading chart data...
G. IUD Insertions: Public vs Private
Loading chart data...
H. Female Sterilization Rate
Loading chart data...
I. Women’s Unmet Need for Family Planning
Loading chart data...
J. Fertile Couples in Family Welfare Programs
Loading chart data...
K. Family Welfare Centers
Loading chart data...
L. Progress of Family Welfare Programs
Loading chart data...
Immunization
A. Vaccinations under the Maternal and Childcare Program
Loading chart data...
B. Infants Given the Oral Polio Vaccine
Loading chart data...
C. Infants Given the Bacillus Calmette Guerin (BCG) Vaccine
Loading chart data...
D. Infants Given Hepatitis Vaccine (Birth Dose)
Loading chart data...
E. Infants Given the Pentavalent Vaccines
Loading chart data...
F. Infants Given the Measles or Measles Rubella Vaccines
Loading chart data...
G. Infants Given the Rotavirus Vaccines
Loading chart data...
H. Fully Immunized Children
Loading chart data...
I. Adverse Effects of Immunization
Loading chart data...
J. Percentage of Children Fully Immunized
Loading chart data...
K. Vaccination Rate (Children Aged 12 to 23 months)
Loading chart data...
L. Children Primarily Vaccinated in (Public vs Private Health Facilities)
Loading chart data...
Nutrition
A. Children with Nutritional Deficits or Excess
Loading chart data...
B. Population Overweight or Obese
Loading chart data...
C. Population with Low BMI
Loading chart data...
D. Prevalence of Anaemia
Loading chart data...
E. Moderately Anaemic Women
Loading chart data...
F. Women with Severe Anaemia being Treated at an Institution
Loading chart data...
G. Malnourishment Among Infants in Anganwadis
Loading chart data...
Sources
Census of India. 2001. District Census Handbook: Hingoli. Office of the Registrar General & Census Commissioner, India.https://censusindia.gov.in/nada/index.php/catalog/27797/download/30966/DH_27_2001_HIN.pdfhttps://censusindia.gov.in/nada/index.php/ca…
George, Mathew. 2023. "The Real Purpose of the Medical College." The Hindu.https://www.thehindu.com/opinion/op-ed/the-real-purpose-of-the-medical-college/article67232008.ecehttps://www.thehindu.com/opinion/op-ed/the-r…
https://pmc.ncbi.nlm.nih.gov/articles/PMC5144115/
M Choksi, B. Patil et al. 2016.Health systems in India.Vol 36 (Suppl 3).Journal of Perinatology.
Mohammed Akhef. 2021. "State’s First Dedicated Antiretroviral Therapy Centre in Hingoli." The Times of India, India.https://timesofindia.indiatimes.com/city/aurangabad/states-first-dedicated-antiretroviral-therapy-centre-in-hingoli/articleshow/84389711.cmshttps://timesofindia.indiatimes.com/city/aur…
National Health Mission (NHM). n.d. "About Accredited Social Health Activist (ASHA)." National Health Mission, India.https://nhm.gov.in/index1.php?lang=1&level=1&sublinkid=150&lid=226#:~:text=One%20of%20the%20key%20components,performing%20her%20spelled%20out%20roles.https://nhm.gov.in/index1.php?lang=1&level=1…
Last updated on 19 October 2026. Help us improve the information on this page by clicking on suggest edits or writing to us.